
Dr. Apurba Kumar Borah, Consultant & HOD, Critical Care Medicine, India
Authors: Dr. Sumanth P1, Dr. Jayanta Padun2
Affiliations:
1 Post graduate trainee year 2, Department of Anaesthesiology, Jorhat medical college and hospital, Jorhat
2 Professor (DACP), Department of Anaesthesiology, Jorhat medical college and hospital, Jorhat
Corresponding and Presenting author:
Dr. Sumanth P
Post graduate trainee year 2
Department of Anaesthesiology
Jorhat medical college and hospital, Jorhat
Email id: sumanthp9900913521@gmail.com
Contact no.: 9900913521
Abstract
Background:
Diphtheria is an acute toxin-mediated infection caused by Corynebacterium diphtheriae, characterized by upper airway inflammation, pseudo membrane formation, and potentially life-threatening airway obstruction. Despite widespread vaccination, sporadic cases continue to occur, particularly in vulnerable populations. Prompt airway management is critical when severe airway compromise develops.
Case Presentation:
A 72-year-old male with known type 2 diabetes mellitus and hypertension presented with acute respiratory distress and diffuse neck swelling. Clinical examination revealed blood pressure 140/110 mmHg, pulse rate 114 bpm, and oxygen saturation of 80% on face mask oxygen. Respiratory examination showed bilateral wheeze, inspiratory stridor, and bilateral crepitations, indicating severe airway compromise and lower respiratory involvement. Neurological
assessment showed GCS E3V3M5 (11/15).
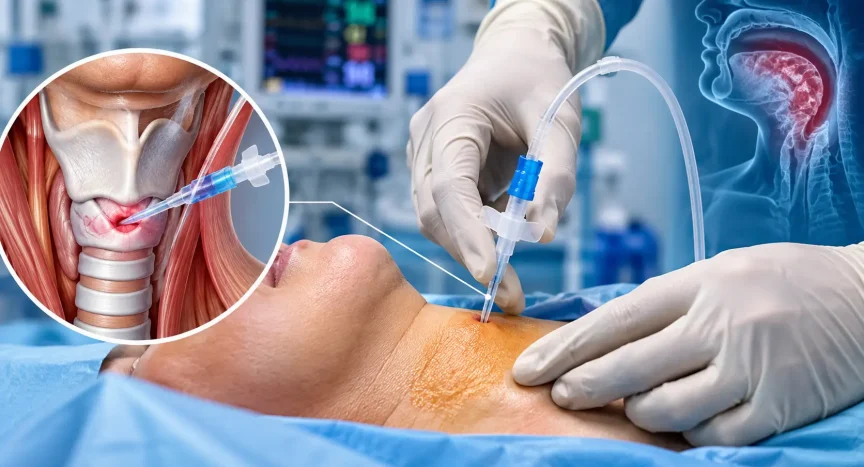
Due to airway compromise and persistently dropping saturation, Emergency Endotracheal intubation attempted and was failed due to difficult airway and pseudo membrane detected on direct laryngoscopy. Emergency cricothyroidotomy using a 16-gauge cannula was performed to establish immediate oxygenation. Following stabilization, awake fibreoptic intubation was successfully performed for definitive airway management, and the patient was connected to
mechanical ventilation in the intensive care unit.
The patient received targeted antibiotic therapy for diphtheria, along with supportive critical care management and control of comorbid conditions. Clinical condition gradually improved, and the patient was successfully extubated after 6 days of mechanical ventilation with stable respiratory parameters.
Conclusion
This case highlights the importance of rapid recognition and staged airway intervention in severe diphtheria-related airway obstruction. Difficult airway guidelines were followed and was found that Emergency cannula cricothyroidotomy can serve as a life-saving bridge to definitive airway management using fibreoptic intubation. Early critical care support and prompt antimicrobial therapy are essential for improving outcomes in such high-risk presentations.
Conflict of Interest:
The Authors declare no conflict of interest
Acknowledgement:
Authors acknowledge the cooperation of ICU nurses, Staff of hospital, Department of Anaesthesiology and General Medicine in providing care for this patient and ensuring early recovery.
References
- World Health Organization. Diphtheria vaccine: WHO position paper. Wkly Epidemiol Rec. 2017;92(31):417–36.
- Anthony S. Fauci, Dennis L. Kasper, Stephen L. Hauser, Dan L. Longo, J. Larry Jameson, Loscalzo J, editors. Harrison’s Principles of Internal Medicine. 21st ed. New York: McGraw-Hill Education; 2022.
- Jonathan Benumof, Carin A. Hagberg. Benumof and Hagberg’s Airway Management. 4th ed. Philadelphia: Elsevier; 2020.
- Difficult Airway Society. Guidelines for management of unanticipated difficult intubation in adults. Anaesthesia. 2015;70(11):1286-1306.


Customer Reviews
Thanks for submitting your comment!